All Posts By

gobesitas

Optimized anaesthesia, optimized pre and postoperative care

By Our research No Comments

One of the things our patients tend to be most concerned about when we discuss bariatric surgery at info meetings and first visits is the anaesthesia. Becoming anesthetized (gastric bypass and sleeve gastrectomy are performed in full anesthesia) is always a feeling of loss of control, you do not know for sure what is going on. Our staff know how you feel and we will take good care of you. We are constantly trying to improve everything we do, and that also applies to the anaesthesia. More than ten years ago, our team published (link no 1) a study on how to make the anaesthesia smoother. Already during this study, we shortened the time from start of anaesthesia to start of operation from 23 minutes<to 8 minutes; And the time from the end of surgery to wake-up from<6 minutes to 2 minutes (!).

ERAS -enhanced recovery after urgery

We have also worked to make patient care after surgery as good as possible. This is done according to evidence-based guidelines, called ERAS (read more here, link No. 2) . The goal is that you as a patient should have as little side effects of the anaesthesia (nausea, etc.) and the actual surgery (pain) as possible.

All of these are examples of our philosophy within the team and the clinic: that everything that can be improved all the time should be worked actively with -and this we hope and believe that you as a patient will also benefit from.

More studies from our team can be seen below!

Bergland O, Bergland A, Gislason H, Rader J. The implementation of the ERAS protocol in high-volume bariatric surgery: complications and anaesthetic considerations in 5068 consecutive morbidly obese patients. Accepted for publication in Acta Anesth.

Karlsson A, Wendel K, Polits S, Gislason H, Hedenbro J. Preoperative nutrition and postoperative discomfort in ERAS settings: A randomized study in gastric bypass surgery. Obes Surg 2016;26:743-748

Link No 1: https://www.ncbi.nlm.nih.gov/pubmed/19025533

Link No 2: www.erassociety.org

Distal gastric bypass and SASI -alternatives to standard operations

By Operating methods, Our research No Comments

The basic operations with us, as in the rest of Sweden, are the surgical procedures gastric bypass and sleeve gastrectomy. These complement each other in a good way, both in terms of advantages, disadvantages and efficiency. For the vast majority it is enough to choose between these two.

But sometimes we see special cases; one example is those with an extra high BMI (BMI above 50). Here, a ”regular” gastric bypass can often be quite sufficient even in the long run -but not always. What to do then?


Alternative options to standard gastric bypass

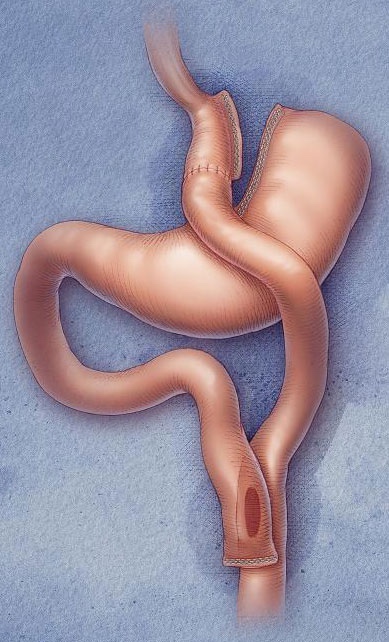
Our surgeon team has researched the alternatives to standard gastric bypass -you will find a list of publications below. In order not to make it all too technical and complicated, one can say that the effectiveness of the surgery can be adjusted based on how long a portion of the intestine is disconnected (if the extra-long section of the bowel is disconnected, it is called a distal gastric bypass) or how long a part that remains from the mini-stomach to the large intestine-thus how many centimeters of small bowel that are exposed to the food after the procedure. The shorter this distance is, the more effective weight loss -but also the higher the risk of side effects.

A new option, at high BMI or when a gastric sleeve does not prove to work fully, is the operation SASI (single anastomosis sleeve ileal bypass). Watch our information video here on our site here for more information on SASI!

We will look at your specific situation in connection with our first visit with checklisting. If you might be eligible for any of our more ”special” procedures, we’ll discuss it with you. Then we also discuss what special things you will need to consider afterwards (for example, more ambitious follow-up with blood tests, etc.).


Scientific work on surgical methods

Leifsson BG, Gislason H. Laparoscopic Roux-en-Y gastric bypass with 2-metre long biliopancreatic limb for morbid obesity: Technique and experience with the 150 first patients. Obesity Surgery 2005;15:35-42.


Nergaard BJ, Leifsson BG, Hedenbro J, Gislason. HG. Gastric bypass with long alimentary limb or long pancreato-biliary limb-Long-term results on weight loss, resolution of co-morbidities and metabolic parameters. Obes Surg 2014;24:1595-1602.


Shah K, Nergard BJ, Fagerland M. Gislason H. Limb length in gastric bypass in super-obese patients – importance of total alimentary small bowel tract. Accepted for publication in Obesity Surgery.


Shah K, Nergard BJ, Fagerland M. Gislason H. Distal gastric bypass – 2 m bilipancreatic limb construction with varying lengths of common channel. Accepted for publication in SOARD.


Canada’s Food Guide-Amazing free resource

By Food and drink No Comments

Canadian Obesity Summit 2019

GB Obesitas Skåne participated in the meeting 6th Canadian Obesity Summit In Ottawa last week. Obesity Canada is a network of healthcare professionals, researchers, policy makers and other people with an interest in the disease obesity.

In conjunction with the meeting, they presented the new version of Canada’s Food Guide -A free online database that contains easily accessible advice, support and tips for those who want to eat and feel as good as possible in their everyday life.

Canada’s Food Guide

You go through:

What food you should choose-more natural food and less processed, drink water instead of sweetened drinks, read on the labels what the food contains before you buy, watch out for what the food advertising contains, and more.

thinking about how to eat: Cook food yourself more often, take your time when you eat, feel when you start to be satisfied, plan your meals in advance, enjoy the food, eat together with others.

Recipes. The Guide has a variety of free recipes of all kinds: breakfast, lunch, dinner, snack. All with variations and tips.

hints and tips for different situations-to eat right on a limited budget, to shop right in the grocery store, food at festivals and parties, training, meal planning, food at school and at work, food for young, adults and the elderly -and more.

further facts -All content is double-checked and adapted to current health research. There are materials to download for health professionals, links to research and the ”Food Guide Snapshot – a short version of the Guide for everyone to be able to use anytime and virtually anywhere.

Your own food guide!

Canada’s Food Guide may just as well be your guide -just browse to their website, address https://food-guide.canada.ca/en and then save the page on the home screen of your smart phone, so that you always have the guide in your pocket with you. Good luck!

Canada’s Food Guide -fantastisk gratis resurs

By Mat och dryck, Prevention av fetmasjukdom, Resurser online No Comments

Canadian Obesity Summit 2019

GB Obesitas Skåne deltog i mötet 6th Canadian Obesity Summit i Ottawa föregående vecka. Obesity Canada är ett nätverk av sjukvårdspersonal, forskare, beslutsfattare och andra människor med intresse för sjukdomen övervikt/fetma.

I samband med mötet presenterades nya versionen av Canada’s Food Guide -en gratis databas online som innehåller lättillgängliga råd, stöd och tips till den som vill äta och må så bra som möjligt i sin vardag.

Canada’s Food Guide

Man går igenom:

vilken mat man bör välja -mer naturlig mat och mindre högprocessad, drick vatten istället för sötade drycker, läs på etiketterna vad maten innehåller innan du köper, se upp för vad matreklamen innehåller, med mera.

-att tänka på hur man äter: laga oftare mat själv, ta tid på dig när du äter, känn efter när du börjar bli mätt, planera dina måltider i förväg, njut av maten, ät tillsammans med andra.

-recept. Guiden har en mängd gratis recept av alla slag: frukost, lunch, middag, mellanmål. Alla med variationer och tips.

råd och tips för olika situationer -att äta rätt med begränsad budget, att handla rätt i livsmedelsbutiken, mat vid högtider och fester, träning, måltidsplanering, mat i skolan och på jobbet, mat för unga, vuxna och äldre -med mera.

fördjupning -allt innehåll är dubbelkollat och anpassat till aktuell hälsoforskning. Det finns material att ladda ned för hälsopersonal, länkar till forskning och ”Food guide snapshot -en kortversion av guiden för alla att kunna använda när som helst och i princip var som helst.

Din egen matguide!

Canada’s Food Guide kan precis lika gärna vara Din matguide -bara surfa in på deras webbadress https://food-guide.canada.ca/en och spara sedan sidan på hemskärmen på din smarta telefon, så har du alltid guiden i fickan med dig. Lycka till!

Distal gastric bypass och SASI -alternativ till standardoperationerna

By Operationsmetoder, Vår forskning No Comments

Basutbudet hos oss, liksom i övriga Sverige, är operationerna gastric bypass och sleeve. Dessa kompletterar varandra på ett bra sätt, både vad gäller för- och nackdelar samt effektivitet. För de allra flesta räcker det att välja mellan dessa två.

Men ibland ser vi ju specialfall; ett exempel är de med extra högt BMI (BMI över 50). Här kan en ”vanlig” gastric bypass ofta vara fullt tillräcklig även i längden -men inte alltid. Vad ska man göra då?


Alternativ till standard gastric bypass

Vårt kirurgteam har forskat på alternativ till standard gastric bypass -du finner en lista på publikationer här nedan. För att inte göra det hela alltför tekniskt och komplicerat kan man säga att effektiviteten i operationen i viss grad kan justeras utifrån hur lång del av tarmen som kopplas ur (om extra långt avsnitt tarm kopplas ur, kallas det en distal gastric bypass) respektive hur lång del som är kvar från lillmagen till tjocktarmen -alltså hur många centimeter tunntarm som exponeras för födan efter ingreppet. Desto kortare detta avstånd är, desto effektivare viktnedgång -men också högre risk för biverkningar.

Ett nytt alternativ, vid höga BMI eller då en gastric sleeve inte visar sig fungera fullt ut, är operationen SASI (single anastomosis sleeve ileal bypass). Titta på vår informationsfilm här på sajten för mer info om SASI!

Vi kommer att gå igenom situationen för just dig i samband med våra nybesök med checklistning. Om du skulle kunna vara aktuell för någon av våra mer ”speciella” ingrepp, så diskuterar vi det med dig. Då tar vi även upp vilka särskilda saker du kommer att behöva tänka på efteråt (exempelvis mer ambitiös uppföljning av blodprover m.m.).


Vetenskapliga arbeten om operationsmetoder

Leifsson BG, Gislason H. Laparoscopic Roux-en-Y gastric bypass with 2-metre long biliopancreatic limb for morbid obesity: Technique and experience with the 150 first patients. Obesity Surgery 2005;15:35-42.


Nergaard BJ, Leifsson BG, Hedenbro J, Gislason. HG. Gastric bypass with long alimentary limb or long pancreato-biliary limb-Long-term results on weight loss, resolution of co-morbidities and metabolic parameters. Obes Surg 2014;24:1595-1602.


Shah K, Nergard BJ, Fagerland M. Gislason H. Limb length in gastric bypass in super-obese patients – importance of total alimentary small bowel tract. Accepted for publication in Obesity Surgery.


Shah K, Nergard BJ, Fagerland M. Gislason H. Distal gastric bypass – 2 m bilipancreatic limb construction with varying lengths of common channel. Accepted for publication in SOARD.


Optimerad sövning, optimerad för- och eftervård

By Narkosen vid operation, Vår forskning No Comments

En av de saker våra patienter brukar vara mest oroliga inför när vi diskuterar kring fetmakirurgi vid infoträffar och nybesök är sövningen. Att bli sövd (gastric bypass och gastric sleeve utförs i full narkos) är alltid en känsla av kontrollförlust, man vet inte säkert vad som händer. All vår personal vet hur du känner och vi kommer att ta väl hand om dig. Vi försöker hela tiden bli bättre på allt vi gör, och det gäller även narkosen. Redan för mer än tio år sedan publicerade vårt team (länk nr 1) en studie på hur man kan göra narkosen smidigare. Redan under denna studies gång förkortade vi tiden från narkosens start till operationens start från 23 minuter till <8 minuter; och tiden från kirurgins slut till väckning från 6 minuter till <2 minuter (!).

ERAS -enhanced recovery after urgery

Vi arbetar sedan tidigare även med att göra vården efter operation så bra som möjligt. Detta sker enligt evidensbaserade riktlinjer, s.k. ERAS (läs mer här länk nr 2) . Målet är att Du som patient skall ha så lite biverkningar av narkosen (illamående m.m.) respektive själva kirurgin (smärta) som möjligt. 

Allt detta är exempel på vår filosofi inom teamet och kliniken: att allt som kan förbättras hela tiden ska jobbas aktivt med -och detta hoppas och tror vi att även Du som patient kommer att ha nytta av.

Fler studier från oss ser du här nedan!

Bergland O, Bergland A, Gislason H, Rader J. The implementation of the ERAS protocol in high-volume bariatric surgery: complications and anaesthetic considerations in 5068 consecutive morbidly obese patients. Accepted for publication in Acta Anesth. 

Karlsson A, Wendel K, Polits S, Gislason H, Hedenbro J. Preoperative nutrition and postoperative discomfort in ERAS settings: A randomized study in gastric bypass surgery. Obes Surg 2016;26:743-748

Länk nr 1: https://www.ncbi.nlm.nih.gov/pubmed/19025533

Länk nr 2: www.erassociety.org

Fast track -kirurgi hos GB Obesitas

By Operationsmetoder, Vår forskning No Comments

Om man kan utföra ett fetmakirurgiskt ingrepp i narkos snabbare utan att kvaliteten går ner, så har man vunnit ett flertal saker: patienten är immobiliserad kortare tid vilket minskar risken för blodpropp; narkosen i sig blir kortare och ger mindre biverkningar. 

Vårt kirurgteam lett av dr Gislason har arbetat med att skapa så smidiga flöden kring operation som möjligt i mer än tio år. Vi har två kirurger som arbetar i såret vid varje operation, vilket minskar operationstiden för gastric bypass /sleeve till i genomsnitt 35 minuter. Bytestiden mellan två patienter på operationssalen blir, tack vare gott lagarbete, 10-15 minuter (i vanlig sjukhusmiljö är bytestiden mellan operationer ofta 30-60 minuter). Detta gör att vi kan operera fler patienter per dag, utan att varje enskild patient på något sätt får sämre vård eller omhändertagande. Det gör det också möjligt för oss att hålla nere priserna på våra privata operationspaket.

Detta fast track -koncept lockar andra team från Europa och övriga världen till oss för att göra studiebesök och lära sig hur man får flödena att fungera bättre på sin hemmaklinik. Dessa studiebesök anordnas i samarbete med Medtronic -kanske just Du får träffa någon utländsk kollega när du är inlagd hos oss!

Konceptet har även beskrivits i forskningsartiklar av vårt team (länk nr 1), och vi har författar kapitel i ämnet i läroböcker för bariatriska kirurger -se nedan!

Gislason H, Jacobsen HJ, Bergland A, Aghajani E, Nergard BJ, Leifsson BG and Hedenbro J. Fast Track in Bariatric Surgery: Safety, quality, teaching aspects, logistics and cost-efficacy in 8000 consecutive cases. Book chapter in: Minimal Invasive Bariatric and Metabolic Surgery. Principles and Technical Aspects. Eds. Lucchese M & Scopinario N. Springer 2015.

Länk 1: https://www.ncbi.nlm.nih.gov/pubmed/22116595